Guide 9 min read
The red eye
How to sort a red eye in the first two minutes: the three questions that flag the dangerous ones, the pattern of redness that localises the problem, and what to look for at each layer from the lids to the anterior chamber.
The pattern, in 5 lines
1. Three questions
Pain, blur, photophobia. Any yes and the eye needs the slit lamp today.
2. The pattern
Diffuse and worst in the fornices, a ring around the cornea, or a deep sector.
3. Lids and conjunctiva
Discharge, follicles, papillae, chemosis, a foreign body under the lid.
4. Cornea
Fluorescein and cobalt blue: a stain means an epithelial defect; a white spot means an infiltrate.
5. Chamber and pupil
Cells, flare, hypopyon; a small pupil in uveitis, a fixed mid-dilated pupil in angle closure.
You will be able to
- Triage any red eye by pain, vision and photophobia.
- Use the pattern of injection to tell conjunctival, ciliary and scleral redness apart.
- Examine the lids, conjunctiva, cornea, anterior chamber and pupil in order, and know what each finding means.
- Recognise the sight-threatening red eyes: keratitis, uveitis, acute angle closure, scleritis, endophthalmitis and orbital cellulitis.
Step one: the three questions
Before the torch, ask. Is it painful, or just gritty and uncomfortable? Is the vision blurred, and does blinking clear it? Does light hurt? Conjunctivitis is gritty, sees normally once the discharge is blinked away, and does not mind light. A yes to real pain, to a blur that does not clear, or to photophobia moves the eye out of the conjunctiva and into the cornea, the anterior chamber or the sclera, and every one of those needs a slit lamp examination the same day. Add three more: contact lens wear, which makes a painful red eye a bacterial keratitis until proved otherwise; trauma, including grinding and hammering, which raises an intraocular foreign body; and recent eye surgery, which makes a painful red eye endophthalmitis until proved otherwise.
Then two observations that cost nothing: is one eye or both involved, because conjunctivitis and allergy are usually bilateral and the dangerous causes usually unilateral; and is the patient sick, with headache, vomiting, fever or a rash, because acute angle closure, orbital cellulitis and herpes zoster all announce themselves that way.
Step two: the pattern of redness
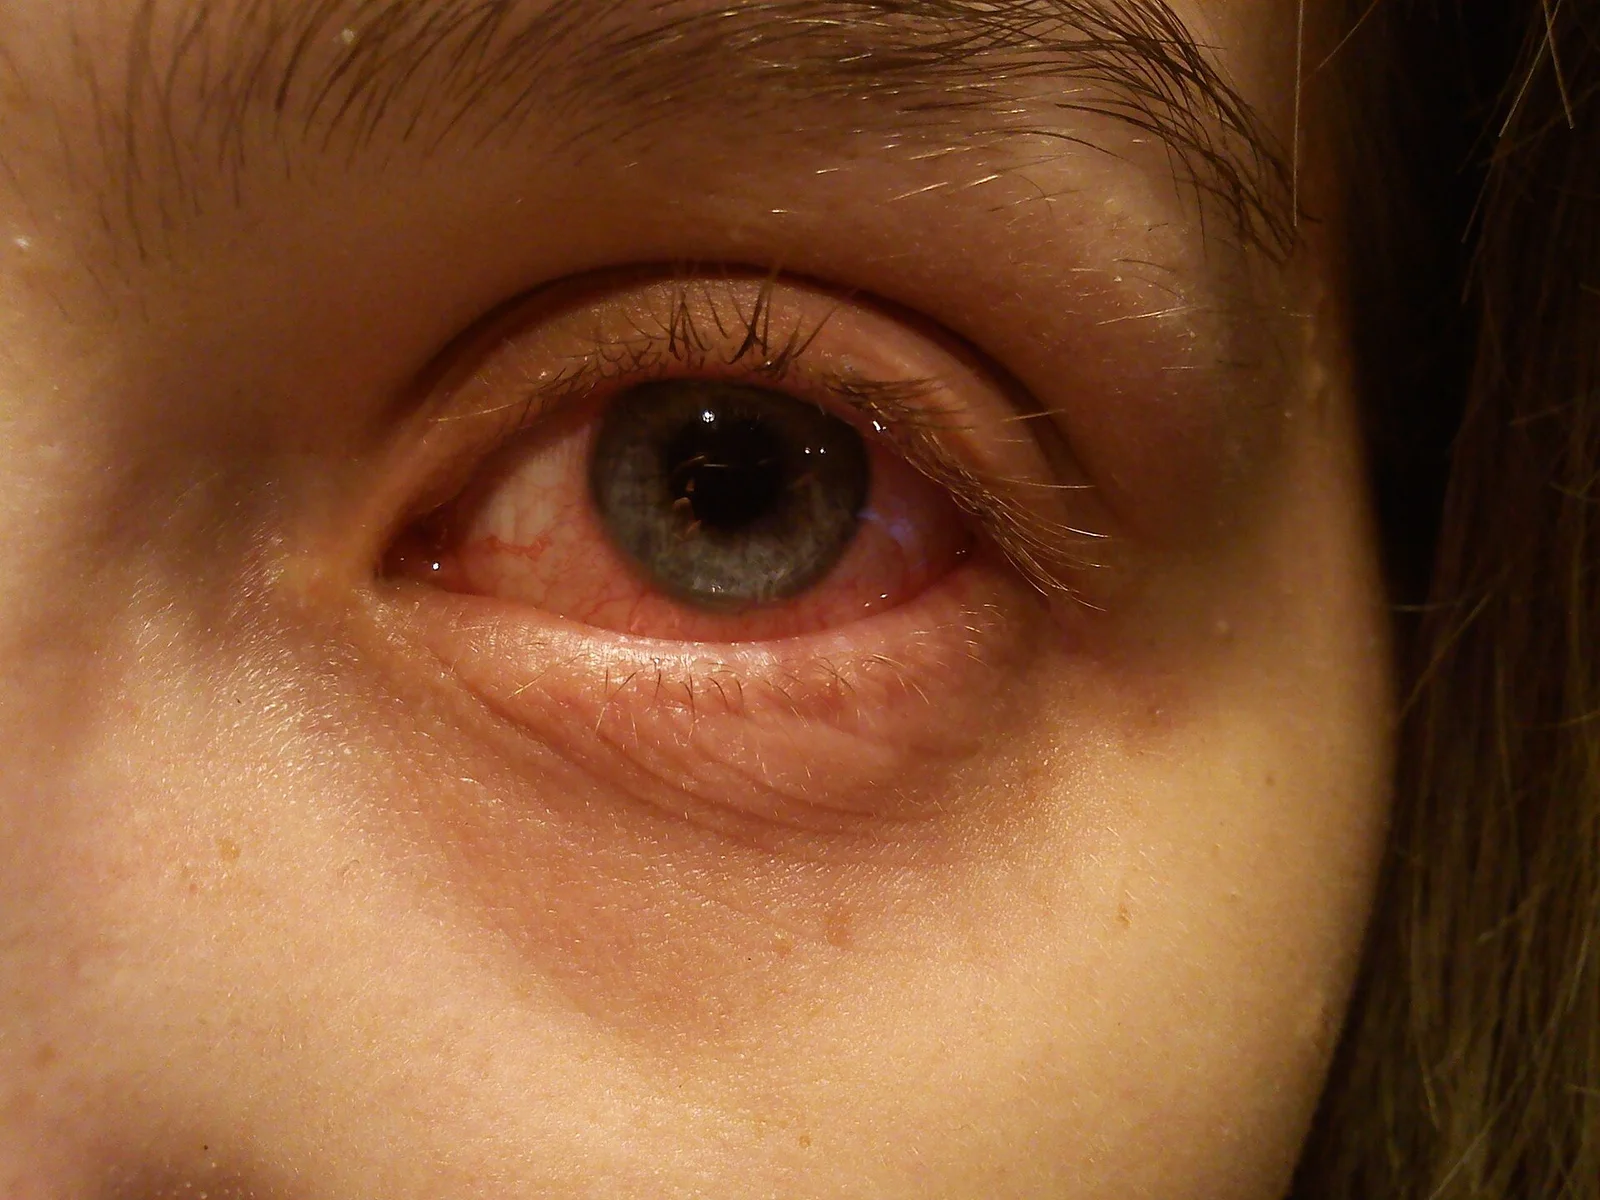
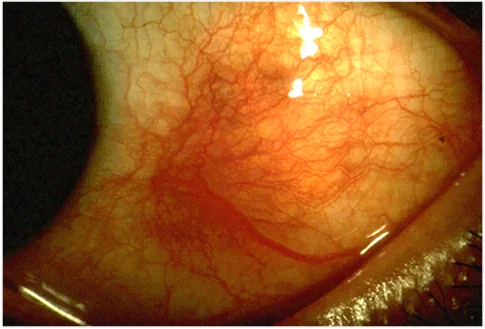
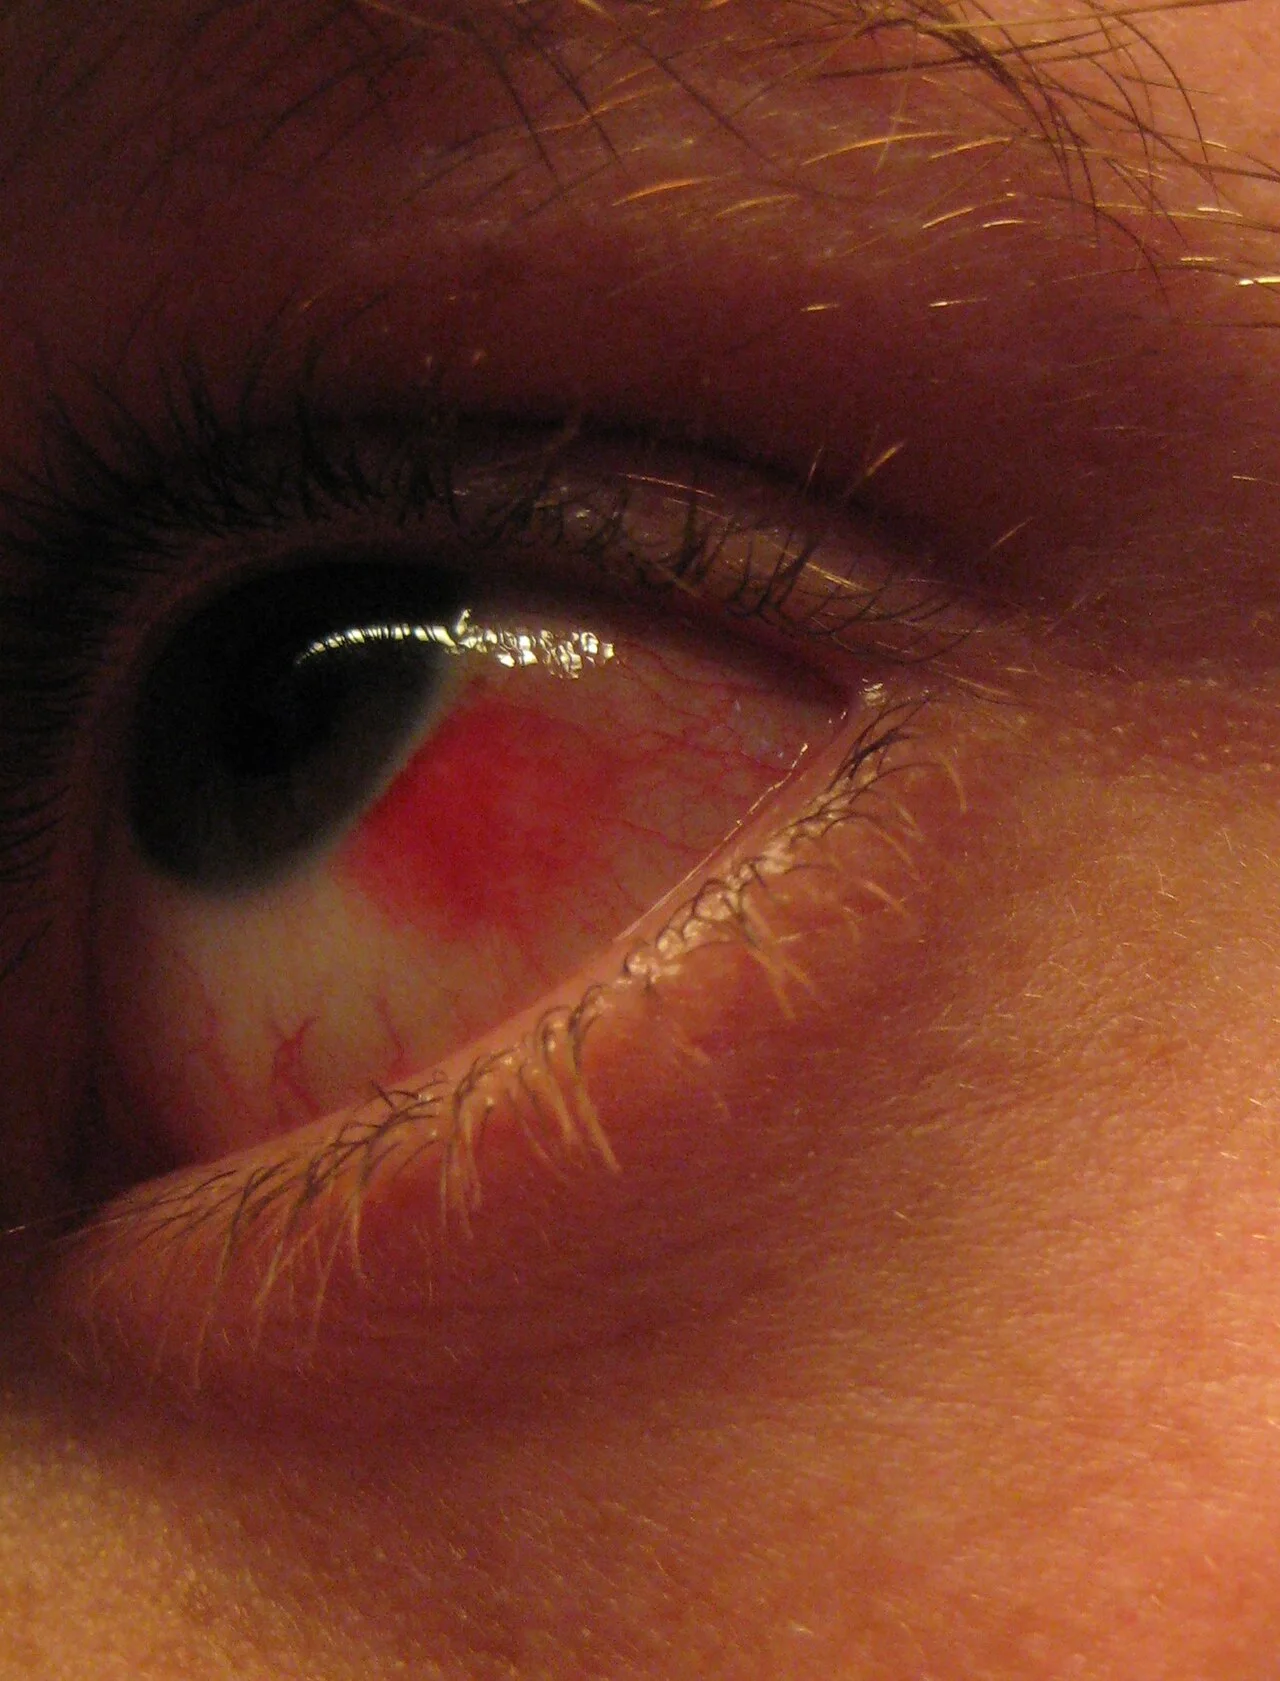
Look at where the redness is worst before you put any drops in. Conjunctival injection is brightest in the fornices and towards the lids, fades towards the cornea, and the vessels move when the conjunctiva is pushed with a cotton bud through the lid. Ciliary injection, or circumcorneal flush, is a violet ring of deep vessels around the limbus that fades towards the fornices, and it means the cornea or the inside of the eye. Scleral injection is deep, bluish red, tender, often in one sector, and the vessels do not move or blanch. A single flat sheet of bright red with a sharp edge and white conjunctiva around it is a subconjunctival haemorrhage, and it is painless.
A drop of phenylephrine settles the harder cases: conjunctival and episcleral vessels blanch within minutes, scleral vessels do not.
| Pattern | Where | Points to |
|---|---|---|
| Conjunctival | Fornices and lids, fading to the limbus; vessels mobile | Conjunctivitis, blepharitis, dry eye, allergy |
| Ciliary flush | A ring at the limbus, fading outwards | Keratitis, anterior uveitis, angle closure |
| Sectoral, superficial | One wedge, bright, blanches | Episcleritis |
| Sectoral or diffuse, deep | Violaceous, tender, does not blanch | Scleritis |
| A flat sheet | Sharp-edged, bright red, painless | Subconjunctival haemorrhage |
Step three: lids and conjunctiva
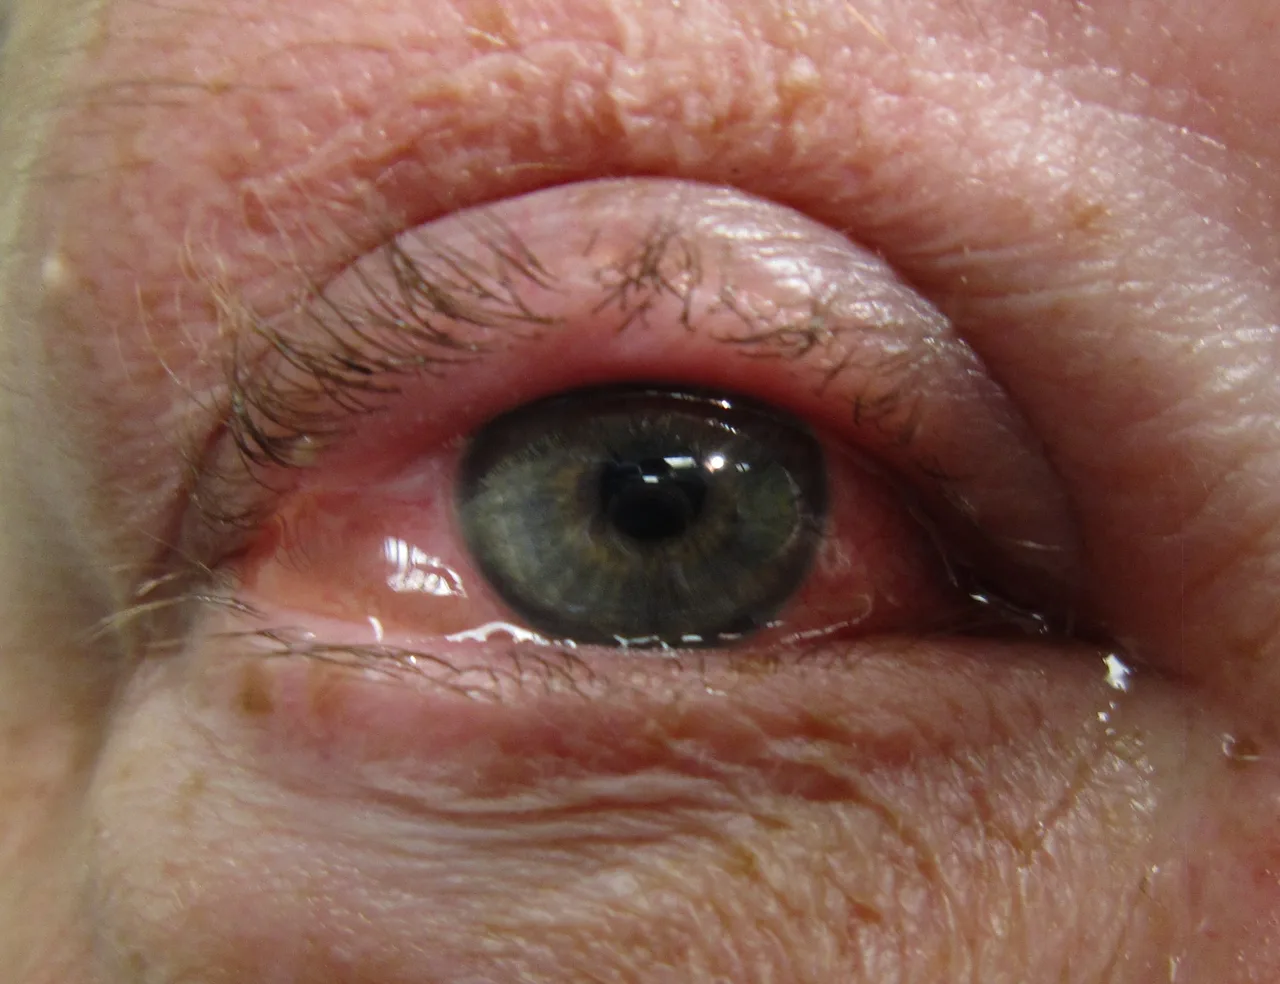
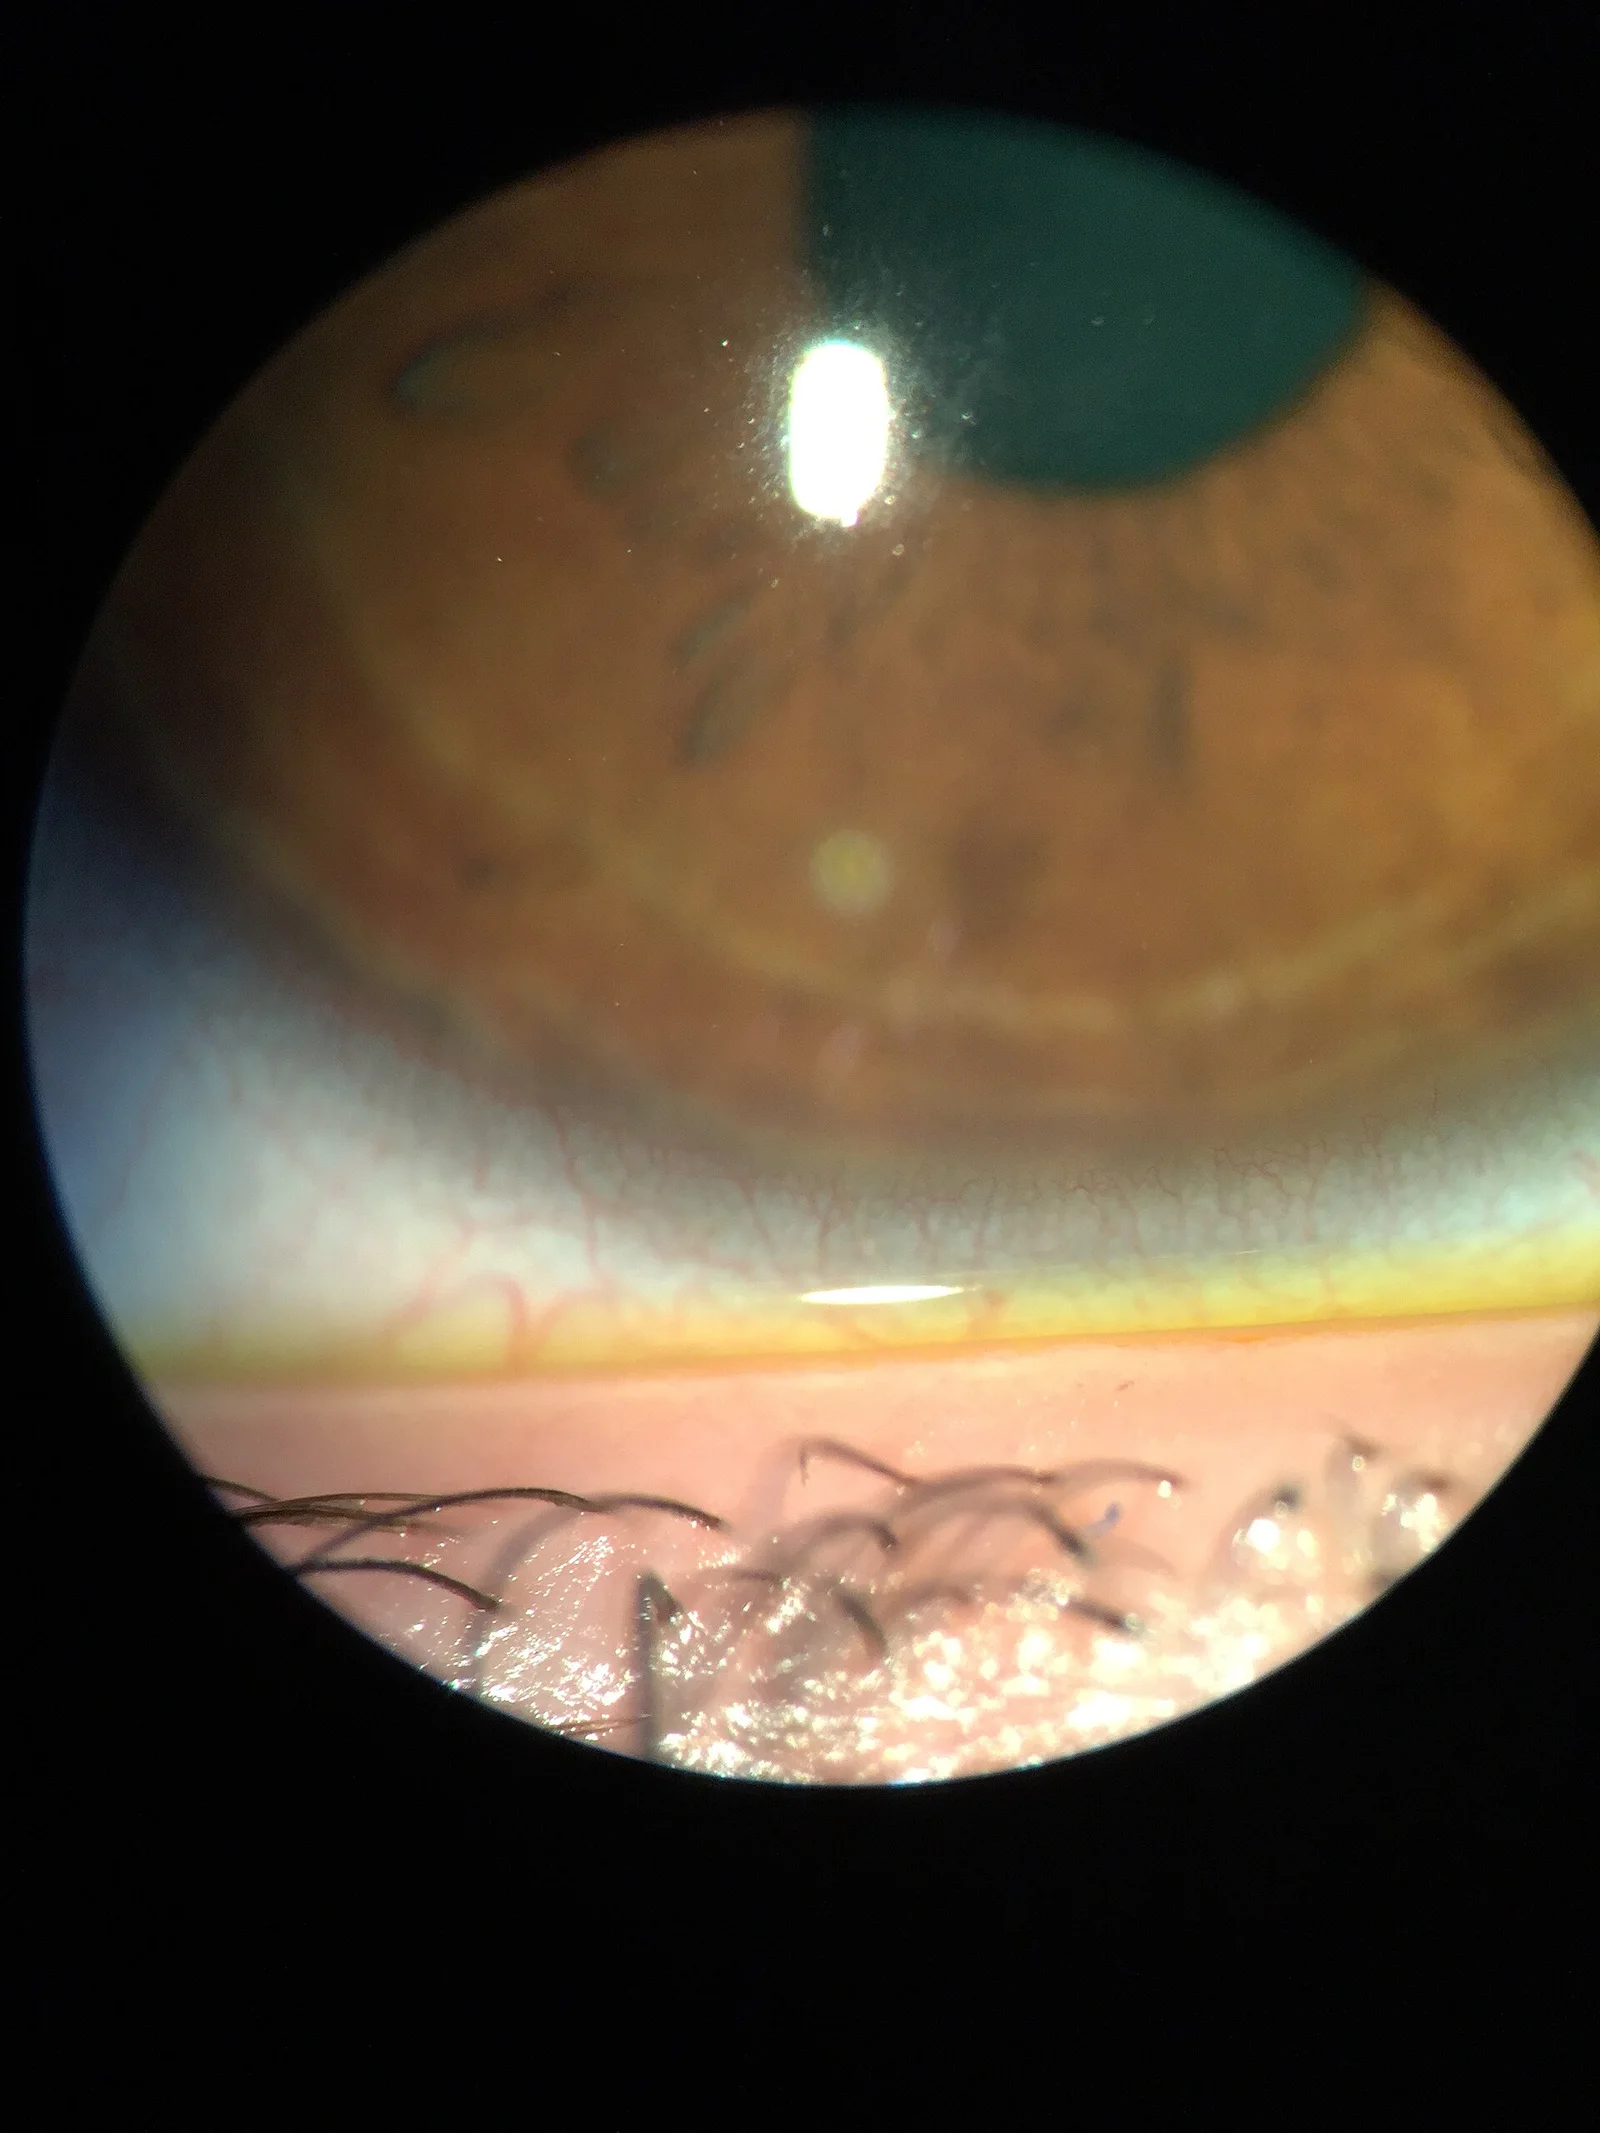
Look at the lid margins for crusting, redness and blocked gland openings, which is blepharitis, the commonest cause of chronically gritty red eyes and easily missed because the eye itself looks nearly normal. Look at the discharge: watery in viral conjunctivitis, mucopurulent and sticking the lids together in the morning in bacterial, stringy and white in allergy, and a copious purulent discharge in a sexually active adult is gonococcal until proved otherwise and can perforate the cornea. Evert the upper lid and look at the tarsal conjunctiva: follicles, small pale bumps like grains of rice, in viral and chlamydial disease; papillae, a red cobbled surface, in allergy and contact lens intolerance; and a foreign body caught under the lid, which is the commonest reason for a corneal scratch that will not heal. Chemosis, the conjunctiva swollen into a glassy jelly, is allergy, or a sign of orbital disease if the eye is also proptosed.
Feel in front of the ear: a tender preauricular lymph node means viral or chlamydial conjunctivitis.
Step four: the cornea
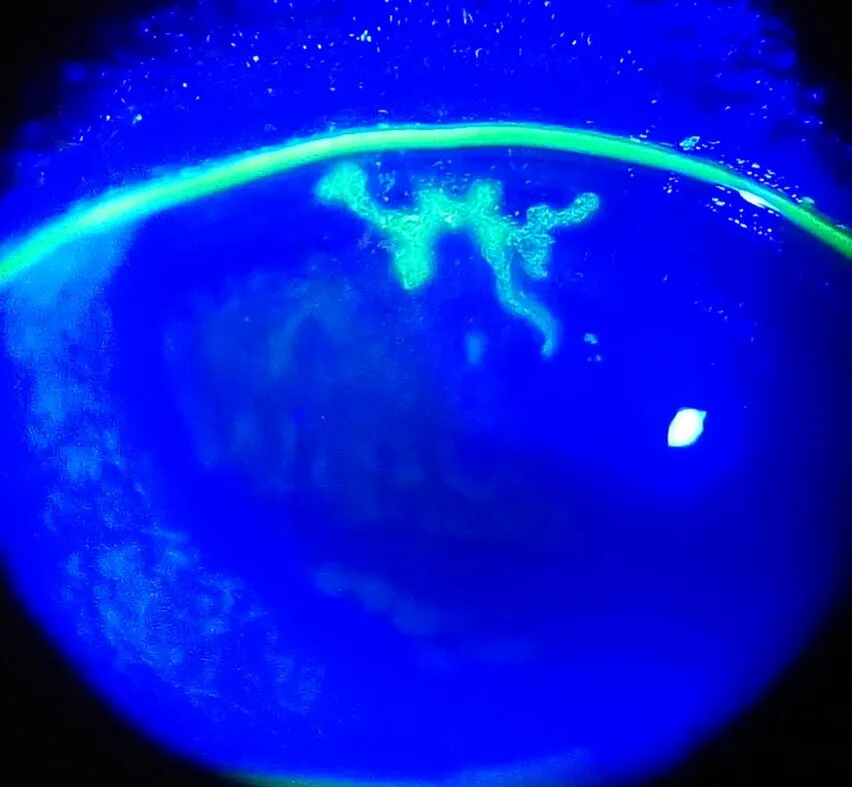
Look at the cornea in white light for clarity, then put fluorescein in and switch to cobalt blue. A bright green stain is an epithelial defect: a sharp-edged patch after trauma is an abrasion, a branching line with knobbed ends is a herpes simplex dendrite, a scatter of fine dots across the lower cornea is exposure or dry eye, and dots across the upper cornea suggest a foreign body under the upper lid. Then look for an infiltrate, a white or grey opacity in the stroma. An infiltrate with an overlying defect in a contact lens wearer is bacterial keratitis; a small peripheral infiltrate with an intact epithelium and a clear gap from the limbus is usually marginal keratitis from staphylococcal blepharitis. A hazy, steamy cornea all over with a hard eye is angle closure. Vesicles on the lid and the tip of the nose with a dendrite that stains poorly is herpes zoster.
Test corneal sensation with a wisp of cotton wool before any anaesthetic drop: reduced sensation points to herpes. If a topical anaesthetic takes the pain away completely, the cause is on the surface; if the deep ache remains, look inside the eye.
Step five: the anterior chamber and the pupil
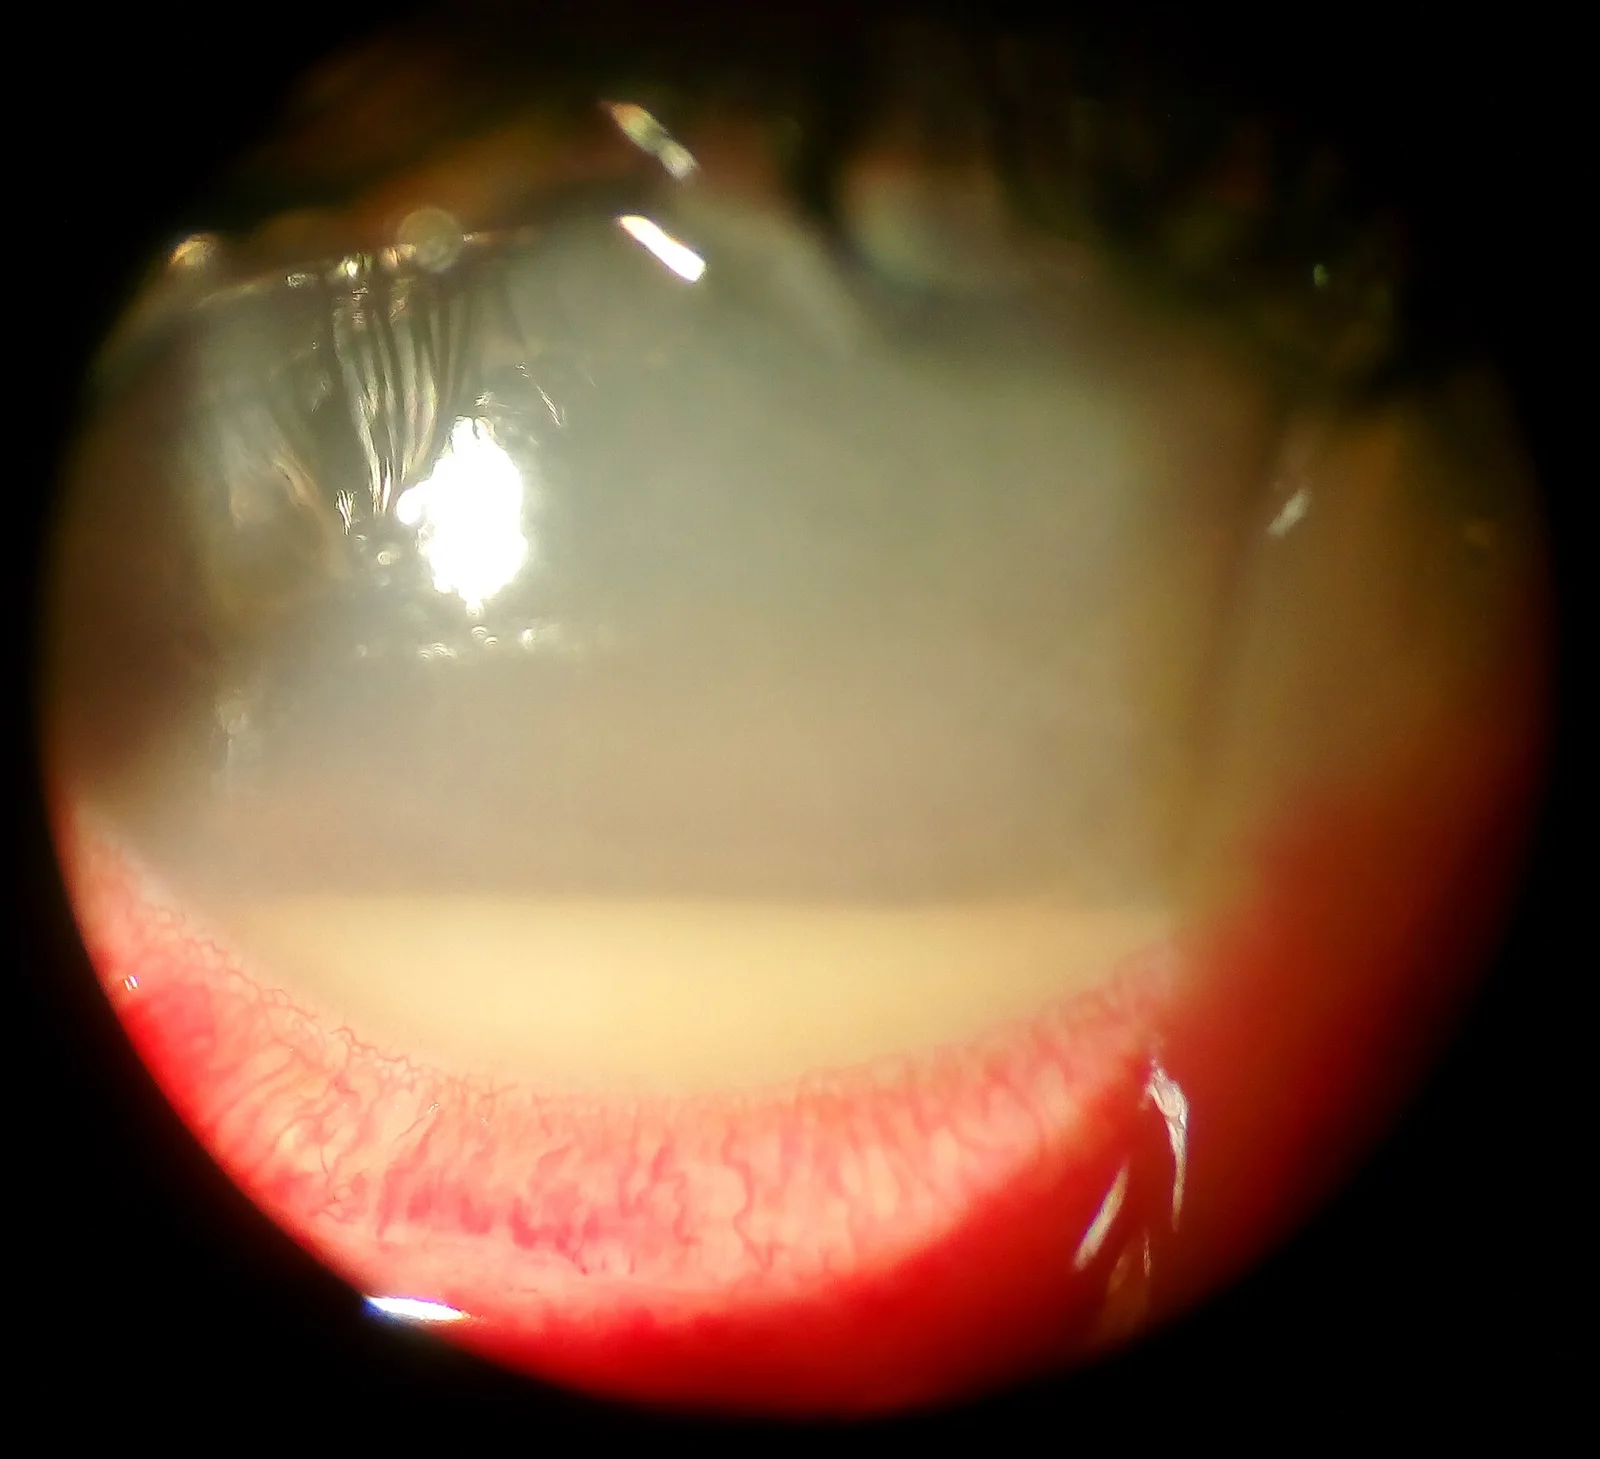
Narrow the slit, angle the arm and focus into the chamber against the dark pupil. Cells drifting through the beam and a smoky flare mean anterior uveitis, and with it come a small, sometimes irregular pupil, photophobia and a deep ache. A white level at the bottom of the chamber is a hypopyon and means severe inflammation: a corneal ulcer, endophthalmitis after surgery, or a violent uveitis. A red level is a hyphaema after trauma. Then judge the depth of the chamber at the edge with a narrow beam or a torch from the side, because a shallow chamber, a fixed mid-dilated pupil, a hazy cornea and a rock-hard eye in a patient with headache and vomiting is acute angle closure, and it needs pressure-lowering treatment within the hour.
The pupil sums up the inside of the eye: small and sluggish in uveitis, fixed and mid-dilated in angle closure, peaked after trauma when the iris has plugged a wound.
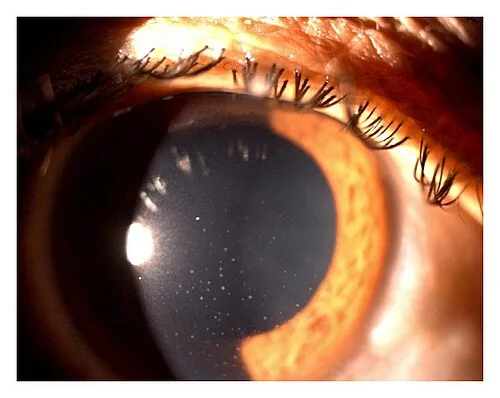
- 1Keratic precipitatesClumps of inflammatory cells stuck to the back of the cornea, settling inferiorly in a triangle (Arlt's triangle) as the aqueous convects.
- 2Finer precipitatesSmaller, dust-like deposits higher up. Fine KPs suggest non-granulomatous uveitis; large greasy 'mutton fat' KPs suggest granulomatous disease.
- 3Corneal light reflexThe lamp's reflection on the tear film. Normal, and a landmark for focusing on the front surface.
- 4IrisThe dilated pupil leaves a crescent of iris at the edge. Look at its margin for posterior synechiae.
The red eyes that cannot wait
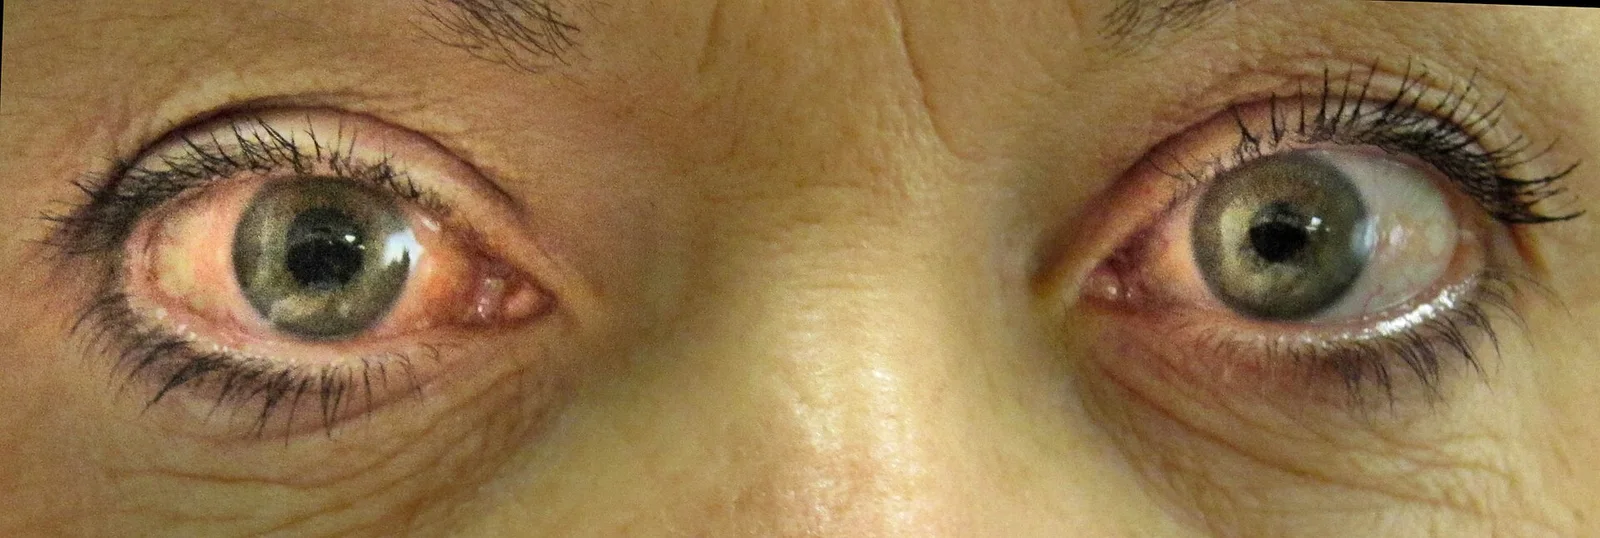
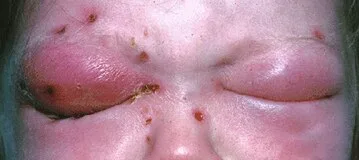
Six diagnoses account for almost every red eye that loses vision, and each has a signature. Bacterial keratitis: contact lenses, pain, an infiltrate that stains. Anterior uveitis: ache, photophobia, small pupil, cells. Acute angle closure: headache, vomiting, hazy cornea, fixed pupil, hard eye. Scleritis: boring pain that wakes the patient, deep injection, tenderness. Endophthalmitis: recent surgery or injection, pain, falling vision, hypopyon. Orbital cellulitis: a swollen hot lid with proptosis, restricted eye movement and fever, especially in a child, and it is a CT scan and intravenous antibiotics today. Herpes zoster ophthalmicus with the nasociliary branch involved, vesicles on the side of the nose, threatens the eye and needs an ophthalmologist.
The rest, conjunctivitis, blepharitis, episcleritis, subconjunctival haemorrhage and dry eye, are managed with reassurance, lubricants and hygiene, and reviewed if they do not settle in a week or if any of the three questions turns to yes.
| Diagnosis | The clue | What happens next |
|---|---|---|
| Bacterial keratitis | Contact lens, pain, white infiltrate that stains | Scrape and intensive antibiotic drops the same day; no patch, no steroid |
| Anterior uveitis | Ache, photophobia, small pupil, cells and flare | Steroid and cycloplegic drops; look for HLA-B27 disease |
| Acute angle closure | Headache, vomiting, hazy cornea, fixed mid-dilated pupil, hard eye | Lower the pressure now; laser iridotomy in both eyes |
| Scleritis | Deep pain that wakes the patient, violaceous, tender | Systemic anti-inflammatory treatment; look for rheumatoid and vasculitis |
| Endophthalmitis | Recent surgery or injection, pain, hypopyon | Vitreous tap and intravitreal antibiotics within hours |
| Orbital cellulitis | Hot swollen lid, proptosis, stiff eye, fever | CT, intravenous antibiotics, watch the optic nerve |
The red eye pathway Examine cells and a hypopyon on the model eye Emergencies
Pearls
- Photophobia that a topical anaesthetic relieves is a surface problem; photophobia that remains is inside the eye.
- A red eye in a contact lens wearer is keratitis until the slit lamp says otherwise.
- One eye, painful, with a small pupil is uveitis; one eye, painful, with a fixed mid-dilated pupil is angle closure.
- Feel the lid with a closed eye: a rock-hard eye and a normal one are easy to tell apart.
Pitfalls
- Prescribing steroid drops for a red eye that has not been examined with fluorescein: a dendrite becomes a geographic ulcer.
- Patching a contact lens wearer's abrasion: the patch incubates the infection.
- Sending home the vomiting patient with a red eye as gastroenteritis.
- Calling scleritis episcleritis because the patient is young: ask whether the pain wakes them.
Ask OphthoSpace about this guide
AI responses are for education and may contain errors. OphthoSpace is not for primary clinical diagnosis.