Guide 9 min read
Interpreting visual fields
How to read a visual field: check that the test is reliable, learn what the greyscale and the probability plots show, then use the midlines, the shape of the defect and its match across the two eyes to place the lesion from the retina to the occipital cortex.
The pattern, in 5 lines
1. Reliability
Fixation losses, false positives, false negatives: is this field worth reading?
2. The plots
Greyscale for the shape; pattern deviation for what is real; the indices for the size.
3. The midlines
A defect that respects the vertical is behind the eye; one that respects the horizontal is in the eye or the nerve.
4. Both eyes
Homonymous or heteronymous, congruous or not: this places a retrochiasmal lesion.
5. Correlate
The field, the disc and the OCT should tell one story; if they do not, one of them is wrong.
You will be able to
- Check the reliability indices of a field test before reading the plot.
- Read a standard automated perimetry printout: greyscale, total and pattern deviation, the global indices.
- Use the vertical and horizontal midlines to separate retinal and optic nerve defects from chiasmal and retrochiasmal ones.
- Recognise the glaucomatous patterns, the bitemporal hemianopia and the homonymous defects, and know where each localises.
What a field test measures
The visual field is everything the eye can see while it looks at one point. A normal monocular field extends about sixty degrees up and in, seventy down and ninety out, with the blind spot fifteen degrees temporal to fixation. Automated perimetry maps the central field, usually the middle twenty four or thirty degrees, by presenting a dim spot at each of a grid of points and finding the faintest one the patient sees. Sensitivity is recorded in decibels: higher means the patient saw a dimmer stimulus, and the field is a hill of vision, highest at fixation and falling to the edges.
The test is only as good as the patient's attention. A first field is often worse than the second because the patient is learning, and a tired, anxious or drowsy patient produces a field full of spurious loss. Read the reliability before the result.
Step one: is the test reliable?
Three indices are printed at the top. Fixation losses: the machine flashes a stimulus in the blind spot from time to time, and a patient who sees it has looked away; more than a fifth is unreliable. False positives: responses when nothing was shown, the trigger-happy patient, and a field full of white spots with sensitivities above normal is the giveaway; above about fifteen per cent, distrust the field. False negatives: a stimulus missed at a point where a much dimmer one was seen earlier, the tired or inattentive patient, though a truly damaged field also produces them. Then look at the test duration and the number of times fixation was checked, and at the patient's pupil size and refraction, because a small pupil or the wrong lens depresses the whole field.
A field with poor reliability is not wrong, it is uninterpretable, and the right response is to repeat it.
- Fixation losses above about 20 per cent: the patient was looking around.
- False positives above about 15 per cent: the patient pressed the button without seeing.
- High false negatives with a normal field: inattention; with a damaged field: possibly genuine.
- A first-ever test: expect a learning effect, and repeat before acting on it.
Step two: the plots
A standard printout shows the same data five ways. The raw sensitivities are the numbers at each point. The greyscale turns them into a picture, darker where sensitivity is lower: it is the plot for shape, and the plot that exaggerates. The total deviation plot compares each point with the age-matched normal and marks the ones that fall below it with probability symbols. The pattern deviation plot does the same after removing any general depression of the whole hill, so that a cataract, a small pupil or a wrong lens no longer darkens everything, and what remains is the localised loss that matters. Read pattern deviation for what is real.
The global indices summarise the field. Mean deviation is the average loss across the field, negative in disease. Pattern standard deviation measures how irregular the loss is: high when there is a localised scotoma, low when the field is uniformly depressed. The glaucoma hemifield test compares the upper and lower halves of the field in mirrored zones, because glaucoma respects the horizontal midline and rarely damages both halves equally at first.
| Plot or index | What it shows | Use it for |
|---|---|---|
| Greyscale | Sensitivity as shades of grey | The shape at a glance; not for deciding what is real |
| Total deviation | Each point against normal for age | Overall loss, including media and pupil effects |
| Pattern deviation | Localised loss after the general depression is removed | The real defect |
| Mean deviation (MD) | Average loss across the field | Severity and progression |
| Pattern standard deviation (PSD) | Irregularity of the loss | Localised versus diffuse damage |
| Glaucoma hemifield test | Upper against lower field | A glaucoma pattern |
Step three: the midlines, and where the lesion is
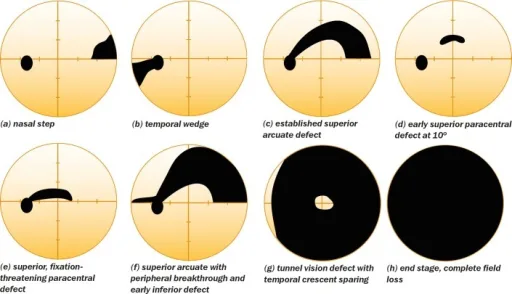
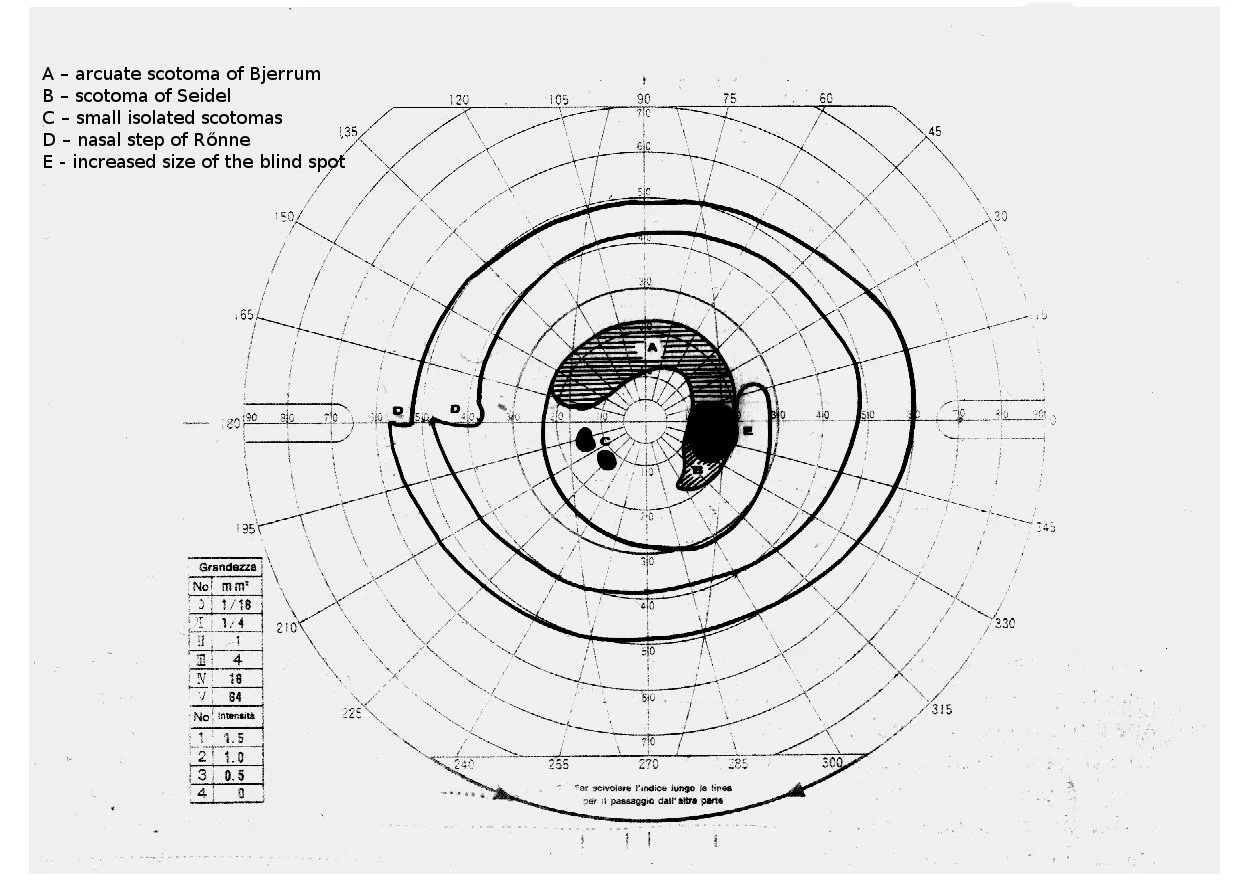
The visual field is organised around two lines, and the lesion sits on one side of each. The vertical midline through fixation divides the field into the halves that are handled by the two sides of the brain: everything to the right of fixation is seen by the left half of each retina and reaches the left occipital lobe. A defect that stops sharply at the vertical midline is therefore at or behind the chiasm. The horizontal midline divides the retina into the upper and lower arcuate nerve fibre bundles, which meet at the temporal raphe without crossing. A defect that respects the horizontal midline, a nasal step or an altitudinal loss, is in the retina or the optic nerve, most often glaucoma or ischaemic optic neuropathy.
Then read the shape. An arcuate scotoma curves from the blind spot around fixation to the nasal horizontal, following a nerve fibre bundle: glaucoma. A central scotoma with the periphery preserved is the macula or the papillomacular bundle: macular disease, optic neuritis, toxic and nutritional neuropathy. An enlarged blind spot is a swollen disc. A generalised constriction with a central island is end-stage glaucoma, advanced retinitis pigmentosa, or, when the island is the same size at every test distance, a functional field.
Step four: the two eyes together
Behind the chiasm every lesion produces a defect in both eyes, so read the fields side by side. A defect on the same side of the vertical midline in both eyes is homonymous: a right homonymous hemianopia means a lesion on the left of the brain, in the optic tract, the lateral geniculate body, the optic radiation or the occipital cortex. The more alike the two eyes' defects, the more congruous, and the further back the lesion: optic tract defects are incongruous, occipital ones nearly identical. An occipital lesion often spares the macula, leaving a few degrees of central field on the blind side. A quadrantanopia points to the radiation: the upper quadrant to the temporal lobe, where the lower fibres loop forward, the lower quadrant to the parietal lobe.
A defect on opposite sides in the two eyes, both temporal fields, is heteronymous: the bitemporal hemianopia of a chiasmal lesion, where the crossing nasal fibres are compressed from below by a pituitary tumour or from above by a craniopharyngioma. A junctional scotoma, a central defect in one eye with a temporal defect in the other, places a lesion where the optic nerve meets the chiasm.
| Defect | Lesion | Notes |
|---|---|---|
| Monocular, respects the horizontal | Retina or optic nerve | Glaucoma, ischaemic optic neuropathy, branch occlusion |
| Monocular central scotoma | Macula or papillomacular bundle | Optic neuritis, macular disease, toxic neuropathy |
| Bitemporal hemianopia | Chiasm | Pituitary adenoma from below, craniopharyngioma from above; image the sella |
| Incongruous homonymous hemianopia | Optic tract | Often with an afferent pupil defect on the side of the temporal field loss |
| Homonymous upper quadrantanopia | Temporal lobe radiation | Meyer's loop |
| Homonymous lower quadrantanopia | Parietal lobe radiation | Often with neglect or other parietal signs |
| Congruous homonymous hemianopia, macula spared | Occipital cortex | Stroke; the pupils and the disc are normal |
Step five: correlate
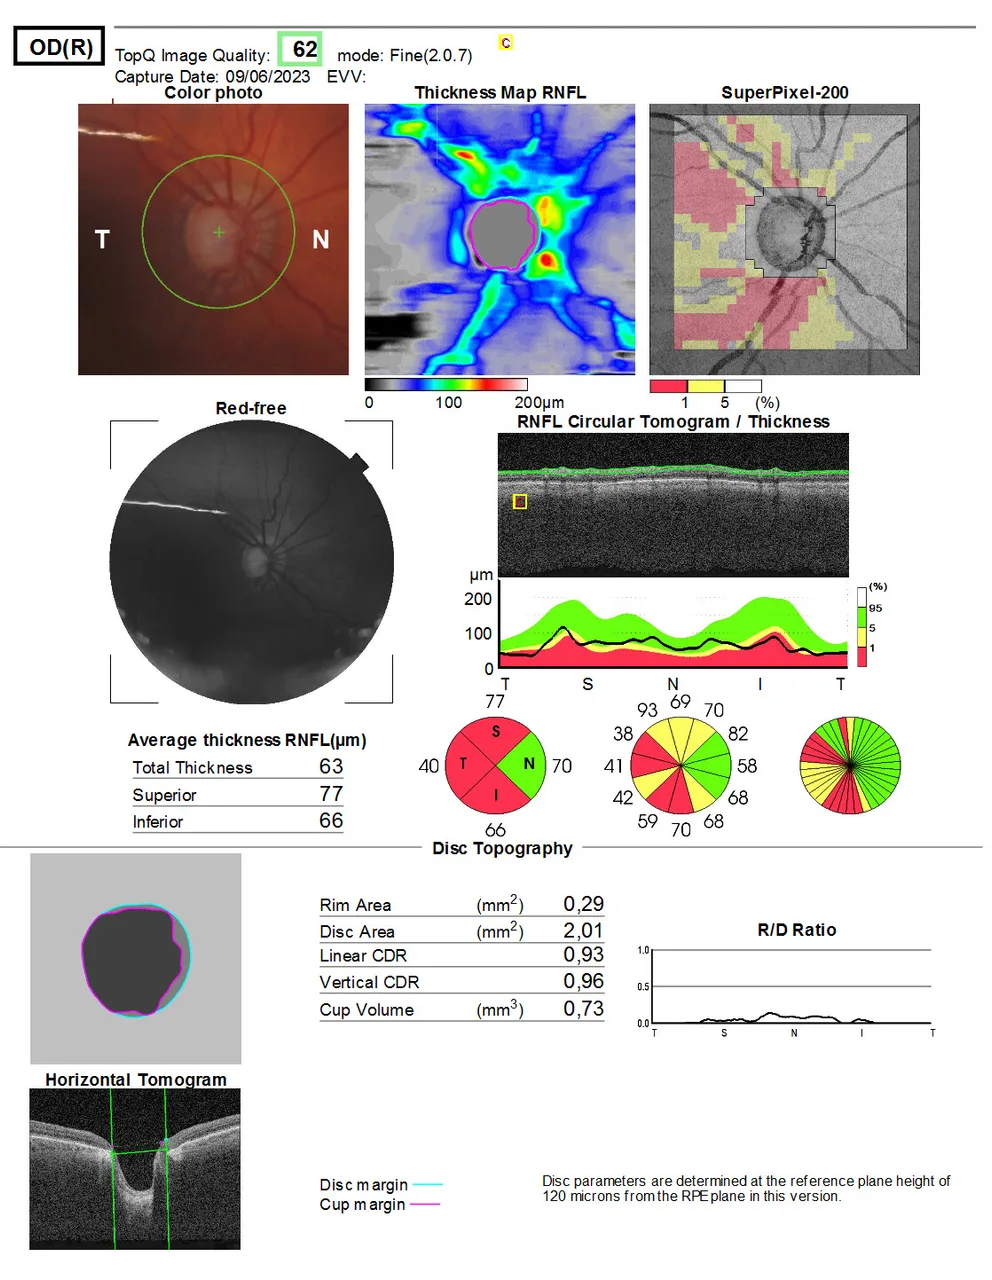
A field is never read alone. In glaucoma the arcuate defect should sit opposite a notch in the disc rim: an inferior rim notch gives a superior arcuate scotoma, and the OCT nerve fibre layer should be thin in the same sector. If the field is worse than the disc, think of a neurological cause or a bad test; if the disc is worse than the field, the field is lagging, and it will follow. In a suspected chiasmal lesion, look for a pale disc and check the pupils. In a homonymous defect, the discs and the pupils are normal and the answer is in the brain, so the next test is imaging, not another field.
Progression is judged on a series, not a pair. Glaucoma is a slow disease, and fields fluctuate; the machine's progression analysis needs several tests over a year or two before a trend means anything.
The visual field lab Field interpretation in the interpret hub The optic nerve, structure by structure The visual pathway
Pearls
- Pattern deviation is the plot that tells the truth; greyscale is the plot that tells a story.
- Respects the vertical: behind the eye. Respects the horizontal: in the eye or the nerve.
- A bitemporal defect means the chiasm: image the pituitary before anything else.
- The more congruous the homonymous defect, the further back the lesion.
Pitfalls
- Reading a field with high false positives as glaucoma.
- Calling a uniformly depressed field a defect when the pupil was small or the lens was wrong.
- Missing a bitemporal hemianopia because each eye was read on its own and each looked like a temporal loss.
- Acting on a single field: repeat, then compare.
Ask OphthoSpace about this guide
AI responses are for education and may contain errors. OphthoSpace is not for primary clinical diagnosis.