Guide 11 min read
Approach to the OCT macula
A layer-by-layer method for the macular OCT: check the scan, find the fovea, walk from the vitreous to the choroid, name the compartment any fluid sits in, then recognise the pattern.
The pattern, in 5 lines
1. The scan
Which eye, where the line runs, and whether the signal is good enough to read.
2. The fovea
Is the pit there, filled in, pulled up, or missing?
3. Front to back
Vitreous and surface, inner layers, outer bands, RPE, choroid: one at a time.
4. Fluid and material
Which compartment, and is there anything bright that should not be there?
5. The pattern
Put the findings together, and check them against the fundus photograph.
You will be able to
- Check a scan for eye, position and quality before reading anything on it.
- Name the retinal layers on a normal B-scan and know which ones matter for vision.
- Localise fluid to the intraretinal, subretinal or sub-RPE compartment, and say what each implies.
- Recognise the common macular patterns: epiretinal membrane, macular hole, central serous, macular oedema, dry and wet degeneration.
What an OCT actually shows
Optical coherence tomography is an ultrasound made of light. A beam of near-infrared light is scanned across the retina and the reflections from each depth are timed by interference, giving a cross section, the B-scan, with a resolution of a few microns. Bright means reflective: tissue that is dense, fibrous or lies across the beam. Dark means transparent or fluid. The image is a map of reflectivity, not of colour or of function, and that is the first thing to keep in mind: a dark space is fluid or a hole, a bright band is a layer that scatters light, and a shadow beneath something bright means the light did not get through.
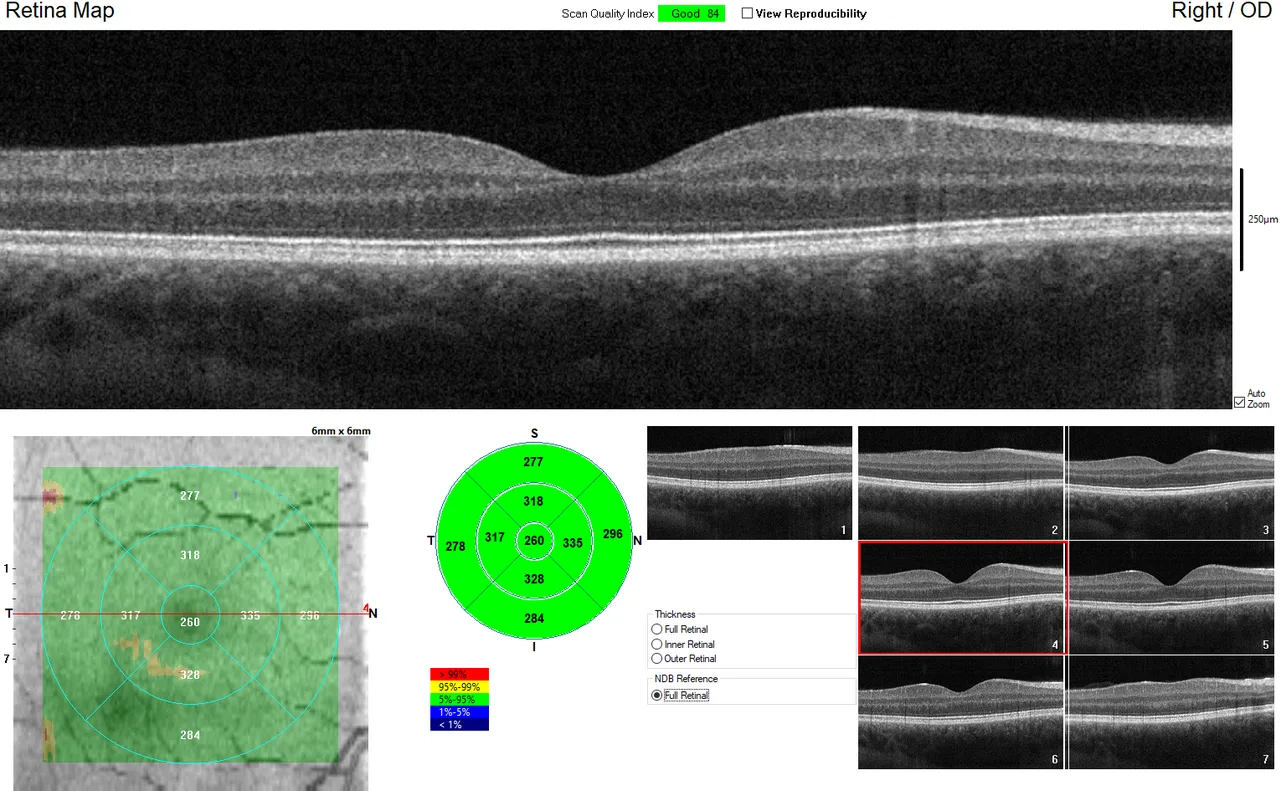
Machines display the B-scan in greyscale or in a false colour scale where red and white are most reflective and blue and black least. Learn to read both. The scan is usually shown alongside an en face image of the fundus with the line of the section drawn across it, and often with a thickness map colour-coded against a normal range.
Step one: check the scan before you read it
Before any finding, confirm four things. Which eye: the report says, and the en face image shows the disc on the nasal side. Where the line runs: a scan that misses the fovea can hide a hole or a blister of fluid entirely, so look at the en face image and make sure the section passes through the centre of the macula. Signal strength: most machines give a number, and a scan below the instrument's threshold blurs the outer bands and can invent thinning. Segmentation: if the machine has drawn the layer boundaries, check that they follow the layers, because a thickness map built on a segmentation that has slipped into a cyst is wrong.
Then orient yourself. The vitreous is at the top of the image, the choroid at the bottom. Temporal is on the right in a right eye scanned left to right, but this varies, so use the disc on the en face image rather than assuming.
- Right or left, and does the disc position on the en face image agree?
- Does the scan line pass through the fovea?
- Is the signal strength above the machine's threshold?
- Do the segmentation lines follow the layers?
Step two: the foveal contour
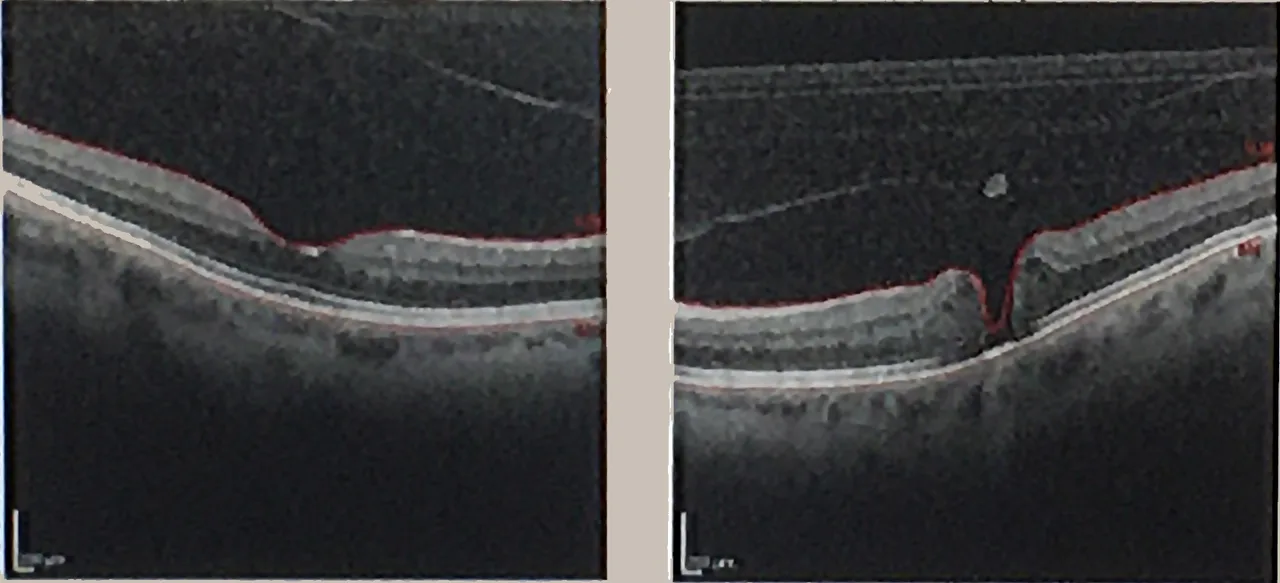
The fovea is the landmark of the whole scan. In a normal eye it is a smooth pit: the inner layers thin away to nothing at the centre so that the outer bands run beneath a shallow depression. Four things can happen to it. It can be filled in, so the pit is shallow or gone: that is thickening, from oedema or a membrane pulling the retina flat. It can be pulled up into a peak by something on the surface. It can be split, with cystic spaces in its walls and a gap in the middle: a hole. Or the whole fovea can be lifted as a dome on a pocket of fluid beneath it.
Say which of these it is before you go further. The contour is the summary of the scan, and it usually points at the diagnosis before the layers confirm it.
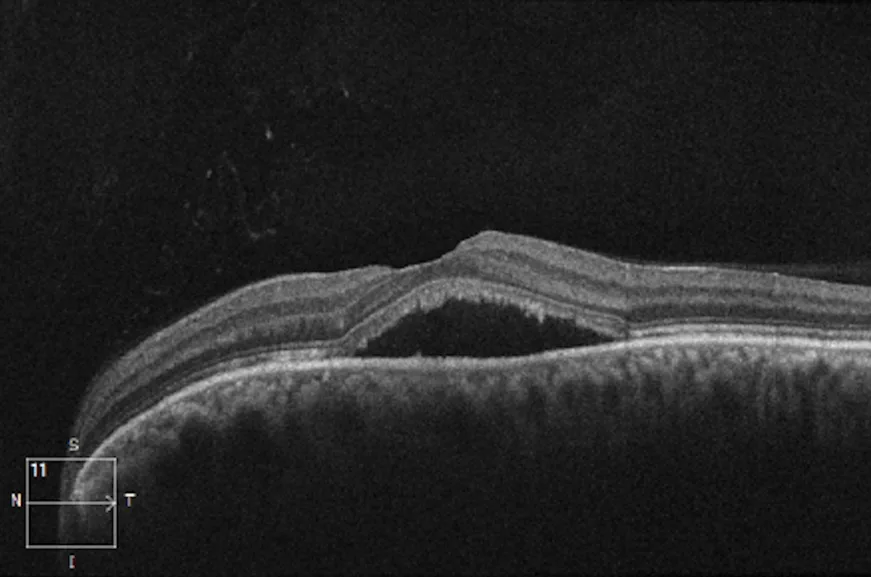
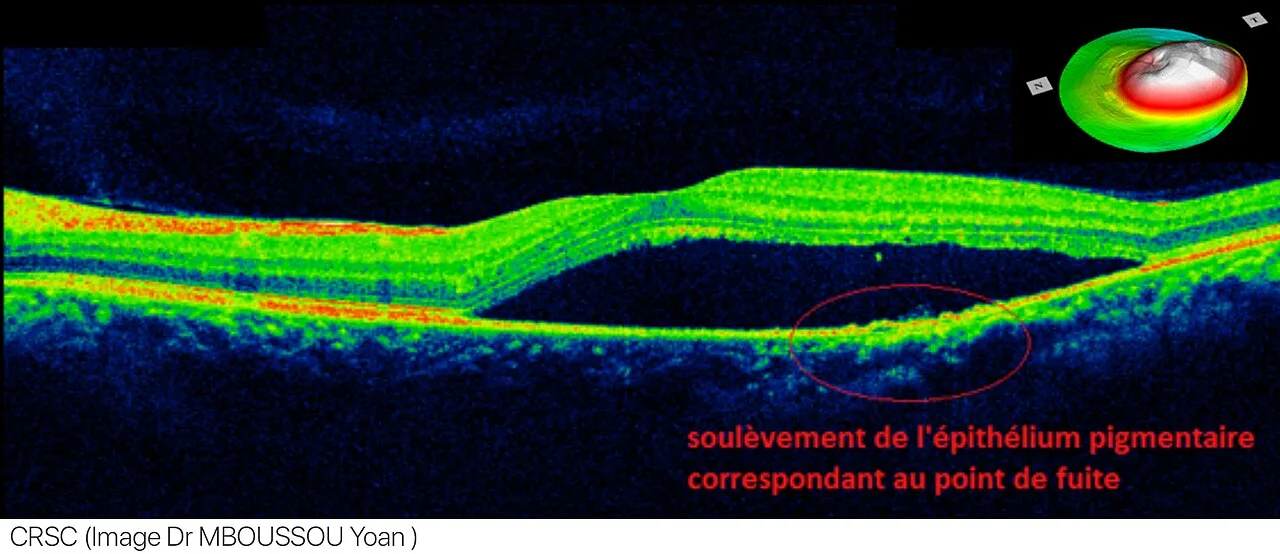
- 1Subretinal fluidAn optically empty (black) space between the neurosensory retina above and the RPE below: the retina has lifted off its pigment epithelium.
- 2Fovea, liftedThe foveal contour is preserved but the whole fovea sits on the dome of fluid, which is why the patient sees a grey smudge.
- 3Retinal pigment epitheliumThe bright continuous band. It is intact here; a break or a bump in it would point to a neovascular membrane instead.
- 4ChoroidThe mottled layer beneath the RPE. Thickened in central serous chorioretinopathy, which is part of why the fluid leaks.
Step three: the layers, from the vitreous to the choroid
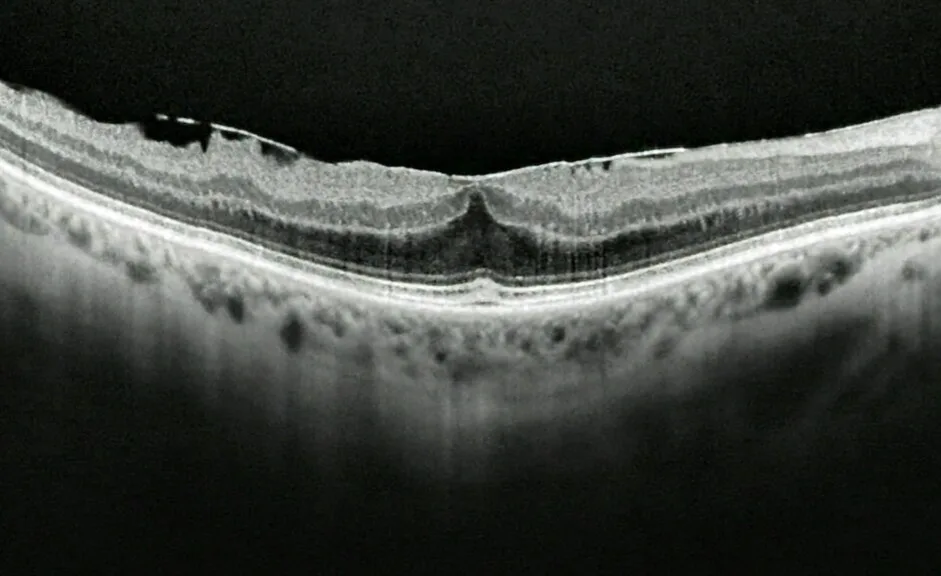
Walk down the scan in order and name what you see. At the top, the vitreous is black; a fine grey line lying on or near the surface is the posterior hyaloid, and where it is still attached at the fovea while separated elsewhere it can pull, which is vitreomacular traction. The retinal surface should be a smooth, continuous, faintly bright line, the internal limiting membrane. A bright irregular sheet on top of it, with the retina puckered beneath, is an epiretinal membrane.
Beneath the surface, the inner retina alternates bright and dark. The nerve fibre layer is bright and thickest towards the disc, the ganglion cell layer darker, the inner plexiform layer bright, the inner nuclear layer dark, the outer plexiform layer bright, the outer nuclear layer dark and thickest under the fovea. Then come the outer bands, which matter most for vision: the external limiting membrane, a thin bright line; the ellipsoid zone, a strong bright line that is the photoreceptor inner segments; and the interdigitation zone against the pigment epithelium. Beneath them the retinal pigment epithelium is the brightest band in the scan, with Bruch's membrane at its base, and under that the choroid, mottled by its vessels, ending at the sclera.
The ellipsoid zone is the line to look for when vision does not match the rest of the scan. Where it is disrupted, the photoreceptors are damaged and the acuity is poor whatever else has been treated; where it is intact under a lesion, vision can recover.
| Layer, top to bottom | Reflectivity | What disease does to it |
|---|---|---|
| Vitreous and posterior hyaloid | Black; hyaloid a faint line | Traction at the fovea; cells in vitritis |
| Internal limiting membrane | Thin bright surface | Epiretinal membrane on it; wrinkling beneath |
| Nerve fibre and ganglion cell layers | Bright then dark | Thin in glaucoma and optic atrophy; thick and bright in artery occlusion |
| Inner nuclear and outer plexiform layers | Dark then bright | Cystoid spaces of macular oedema live here |
| Outer nuclear layer | Dark, thick under the fovea | Thins in atrophy; cysts in some dystrophies |
| External limiting membrane and ellipsoid zone | Two bright lines | Disruption means photoreceptor loss and poor vision |
| Retinal pigment epithelium | The brightest band | Bumps (drusen, PED), breaks, loss (atrophy) with a bright choroid beneath |
| Choroid | Mottled, vessels dark | Thick in central serous; thin in myopia and age |
Step four: fluid, and which compartment it is in
Fluid is black on OCT, and where it sits is the diagnosis. Intraretinal fluid forms round or oval cystoid spaces within the layers, mostly the inner nuclear and outer plexiform layers, separated by bright septa: the pattern of diabetic macular oedema, vein occlusion, uveitic oedema and the oedema after cataract surgery. Subretinal fluid is a single smooth pocket between the outer retina and the pigment epithelium, lifting the retina as a dome: central serous chorioretinopathy when the RPE is intact and the choroid thick, a neovascular membrane when there is bright material or a break in the RPE beside it, and retinal detachment when it extends beyond the macula. Sub-RPE fluid lifts the pigment epithelium itself off Bruch's membrane as a pigment epithelial detachment: a dome whose roof is the bright RPE line.
Say the compartment out loud in the report. It decides the treatment: intraretinal and subretinal fluid in age-related degeneration is injected; subretinal fluid under an intact RPE in a young patient is usually watched; a pocket of fluid with a tear in the retina is a surgical problem.
| Compartment | Looks like | Think of |
|---|---|---|
| Intraretinal | Cystoid spaces within the layers, with septa | Diabetic macular oedema, vein occlusion, uveitis, post-operative oedema, wet AMD |
| Subretinal | A smooth dark pocket between retina and RPE | Central serous, wet AMD, retinal detachment |
| Sub-RPE | A dome with the bright RPE as its roof | Pigment epithelial detachment: serous, drusenoid or fibrovascular |
Step five: bright things that should not be there
After the dark spaces, look for bright ones. Hard exudates are small, very bright dots in the outer plexiform layer, each casting a shadow, and mark chronic leakage. Hyper-reflective material under the retina or under the RPE, especially when it is irregular and beside fluid, is a neovascular membrane or its scar. Drusen are bumps of medium reflectivity under the RPE. A bright thickened inner retina with the outer layers obscured beneath is the acute phase of a retinal artery occlusion. Bright dots scattered through the vitreous are cells.
Shadowing is a sign in itself: something dense enough to shadow is a vessel, an exudate, a haemorrhage or pigment, and the shadow points to where it lies.
Step six: put the pattern together
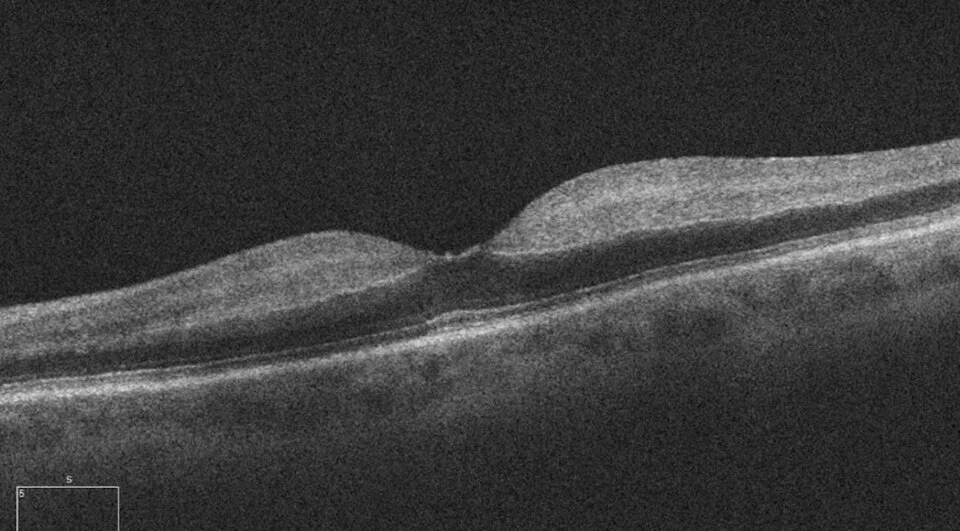
A scan is read layer by layer, but it is diagnosed as a whole. Epiretinal membrane: a bright surface line, wrinkling, a filled-in fovea, thickening without cysts. Vitreomacular traction: the hyaloid attached at the fovea and tenting it up. Macular hole: a full thickness gap with cystic edges; a lamellar hole is a partial defect with the outer layers intact. Central serous: a dome of subretinal fluid under an intact RPE in a young patient, with a thick choroid. Diabetic macular oedema: cystoid intraretinal spaces with hard exudates, often with subretinal fluid at the fovea. Dry AMD: drusen as RPE bumps, then atrophy where the RPE is gone and the choroid beneath shines brightly. Wet AMD: fluid in any compartment with a break or bump in the RPE and bright material beside it.
Then check the scan against the fundus photograph and the patient. A hole that looks small on OCT is a large scotoma to the patient; a dramatic membrane may cause no symptoms at all. The two images answer different questions, and the history answers a third.
Read OCT in the interpret hub The macula, structure by structure Macula in the retina topic
Pearls
- Find the ellipsoid zone under the fovea first: if it is intact the eye can see, whatever else is going on.
- Name the compartment of any fluid before naming the disease.
- A thick choroid with subretinal fluid in a young patient is central serous; a thin choroid with drusen and fluid in an old one is wet degeneration.
- Compare with the last scan. A change of a few microns in the same compartment means more than any single number.
Pitfalls
- Reading a scan that missed the fovea, and calling it normal.
- Trusting a thickness map whose segmentation has slipped into a cyst.
- Calling every dark space a cyst: a shadow under a bright vessel or exudate is not fluid.
- Forgetting the vitreous: traction at the fovea explains many odd contours.
Ask OphthoSpace about this guide
AI responses are for education and may contain errors. OphthoSpace is not for primary clinical diagnosis.